정책·산업 자료 · 원문 해설Policy & industry material · Source-based guide
국내·외 비대면 진료 현황진단 및 쟁점분석Domestic and international telemedicine: status and policy issues
김용희의 원문 역할: 참여연구원Yonghee Kim’s documented role: Participating researcher

연구 내용Overview
국내외 비대면 진료의 제도와 서비스를 검토하고 의료계·산업계·환자 및 소비자단체·법조계·정부의 의견을 비교한 보고서입니다. 당시의 합의 가능 사항과 추가 논의 과제를 정리하며, 현재의 의료제도나 임상 효과를 설명하는 자료로 읽어서는 안 됩니다.
This report reviews telemedicine services and policy and compares views from medical, industry, patient, consumer, legal and government stakeholders. It records areas of potential agreement and unresolved questions in 2022, rather than current clinical guidance.
원보고서의 문제의식·분석·제안을 정리한 해설입니다. 수치는 표시한 표와 쪽을 기준으로 읽습니다. 아래 표는 핵심 항목을 웹에서 읽도록 재구성했고, 원문 표·그림이 있는 페이지를 함께 제공합니다.This reading guide explains the report’s questions, analyses, and proposals in new wording. Tables below re-present selected source results for web reading, alongside images of the relevant original pages.
핵심부터 읽기Start with the main findings
- 보고서는 비대면 진료를 하나의 찬반 질문으로 묶지 않는다. 진료 대상, 초·재진, 병원 범위, 개시 결정, 책임·설명, 수가, 장비와 정보 보호는 서로 다른 합의 수준을 보인다. 2022년 이해관계자 자문에 기반한 단계적 제도화 검토라는 성격이 핵심이다.The report separates eligible conditions, first/follow-up visits, provider scope, initiation, liability, payment, equipment and privacy. Agreement varies by issue. Its core is a historical 2022 consultation-based review of staged institutionalization.PDF 파일 50, 65, 67, 68, 69쪽PDF pages 50, 65, 67, 68, 69
- 한시 허용의 352만여 건은 청구된 진료 건수로 고유 환자 수가 아니다. 의원급이 건수의 78.9%, 진찰료의 77.0%를 차지한 것은 이용·지출 구성의 기록이며 그 자체가 치료 효과·안전성·전달체계 영향을 인과적으로 입증하지 않는다.The approximately 3.52 million claims are visits, not unique patients. Clinic shares of 78.9% of visits and 77.0% of fees describe use and spending, not causal proof of clinical safety, effectiveness or system impact.PDF 파일 38, 39, 40, 43쪽PDF pages 38, 39, 40, 43
- 안전성 확보와 접근성 확대는 같은 방향만을 갖지 않는다. 재진·경증·만성질환 중심의 최소 도입과 중증·거동불편 환자의 접근, 상급기관의 예외 역할을 나누어 검토한다. 이 당시 제안을 현재 이용자에게 적용되는 의료 안내로 읽지 않아야 한다.Safety restrictions and access goals create trade-offs. The proposal distinguishes minimum follow-up/mild/chronic scope from access for severe or mobility-limited patients and exceptions for higher-level institutions. These historical options are not present-day patient guidance.PDF 파일 67, 68, 70쪽PDF pages 67, 68, 70
연구의 배경과 질문Context and question
코로나19로 전화상담·처방이 한시적으로 허용되고 여러 시범사업이 진행되는 상황에서, 비대면 진료를 어떤 조건으로 제도화할 것인지가 이2022년 보고서의 질문이다. 접근성과 편리성의 확대라는 기대와 안전성·의료전달체계·개인정보에 대한 우려를 함께 다룬다. 의료서비스가 디지털화된다는 전망만으로 제도 확대를 당연시하지 않고 이해관계자 사이에 합의 가능한 범위와 남은 쟁점을 나누려는 목적이다. 제출문은 대한민국의학한림원의 협조를 받은 공동 연구라고 명시하며 김용희는 참여연구원으로 기재한다.
This May 2022 report asks under what conditions telemedicine could be institutionalised after temporary telephone consultation and prescribing during COVID-19. It considers access and convenience alongside safety, delivery-system and privacy concerns. Its purpose is to separate potential agreement from unresolved issues rather than assume that digitalisation automatically justifies expansion. The submission identifies cooperation with the National Academy of Medicine and lists Yonghee Kim as a participating researcher.
PDF 파일 2, 3, 5, 6쪽PDF pages 2, 3, 5, 6
국내 추진현황과 근거의 성격Domestic landscape and evidence
국내 현황은 한시적 허용, 의료취약지·재외국민·원양선박·교정시설 등 제한된 시범사업과 서비스 사례로 구성된다. 보고서가 인용한2020년2월~2021년9월276만 건 등 이용실적은 당시 외부 집계이며 연구진이 새로 수행한 임상시험의 성과가 아니다. 보고서는 시범사업이 접근성 개선에 기여할 수 있다는 가능성과 종료 후 평가·지속 운영의 법적 근거가 부족하다는 문제를 함께 설명한다. 진료량의 증가, 이용 만족도, 안전성과 치료 효과는 서로 다른 지표이므로 하나로 묶어 성공했다고 표현하지 않는다.
The domestic review covers temporary permission and pilots for underserved areas, overseas residents, seafarers and correctional facilities. Utilisation totals quoted for 2020–2021 are historical external aggregates, not results of a new clinical trial conducted by the team. The report discusses both access opportunities and gaps in evaluation and continuity after pilots. Volume, satisfaction, safety and treatment effectiveness are different outcomes and should not be merged into a single claim of success.
PDF 파일 5, 6, 28, 37쪽PDF pages 5, 6, 28, 37
해외 제도의 비교International comparison
해외 사례에서는 원격의료가 허용되는지뿐 아니라 보험 적용, 진료 장소·대상, 방식, 면허·개인정보 규정과 코로나19 특례를 구분해 살핀다. 예컨대 미국 사례도 연방의 메디케어와 주별 메디케이드를 나누어 서술한다. 비교의 의미는 어느 나라가 더 선진적이라는 순위를 만드는 것이 아니라 같은 비대면 진료라는 말 아래 적용 조건이 크게 다름을 보여주는 데 있다. 따라서 외국의 제도를 한국에 그대로 도입하면 같은 결과가 발생한다는 근거로 사용하지 않으며, 당시 예외조치를 현재의 상시 제도로 바꾸어 설명하지 않는다.
The international comparison distinguishes insurance, location and patient eligibility, communication modes, licensing, privacy and pandemic exceptions. Even the US discussion separates Medicare from state Medicaid arrangements. The point is to show different institutional conditions behind the same telemedicine label, not rank countries. A foreign rule does not establish that importing it will reproduce an outcome in Korea, and temporary pandemic arrangements should not be redescribed as today’s permanent rules.
PDF 파일 16, 28, 37쪽PDF pages 16, 28, 37
의견수렴 설계와 이해관계 차이Stakeholder consultation
의학한림원 원격의료연구특별위원회와 함께 정부·의료계·산업계·환자 및 소비자단체·법조계의 쟁점을 정리하고2022년4~5월 분야별 FGI를 진행했다.5월26일에는 세미나로 제도화 방향을 논의했다. 질문은 진료 대상, 주체, 책임·면책, 수가, 개인정보, 시설·장비에 걸쳐 있다. 이 절차는 이해관계별 이유와 갈등 구조를 파악하기 위한 질적 의견수렴이며 전체 국민의 찬반 비율을 추정하는 확률표본 조사가 아니다. 각 집단 내부의 모든 구성원이 같은 입장이라는 뜻도 아니다.
Consultations with government, medical, industry, patient/consumer and legal participants took place in April–May 2022, followed by a seminar on 26 May. Questions covered eligibility, providers, liability, payment, privacy and equipment. This qualitative process maps reasons and tensions between stakeholder positions. It is not a probability survey estimating national support, nor evidence that every member within a stakeholder category holds the same view.
PDF 파일 50, 59, 65쪽PDF pages 50, 59, 65
합의 가능 사항과 이견Potential agreement and disagreement
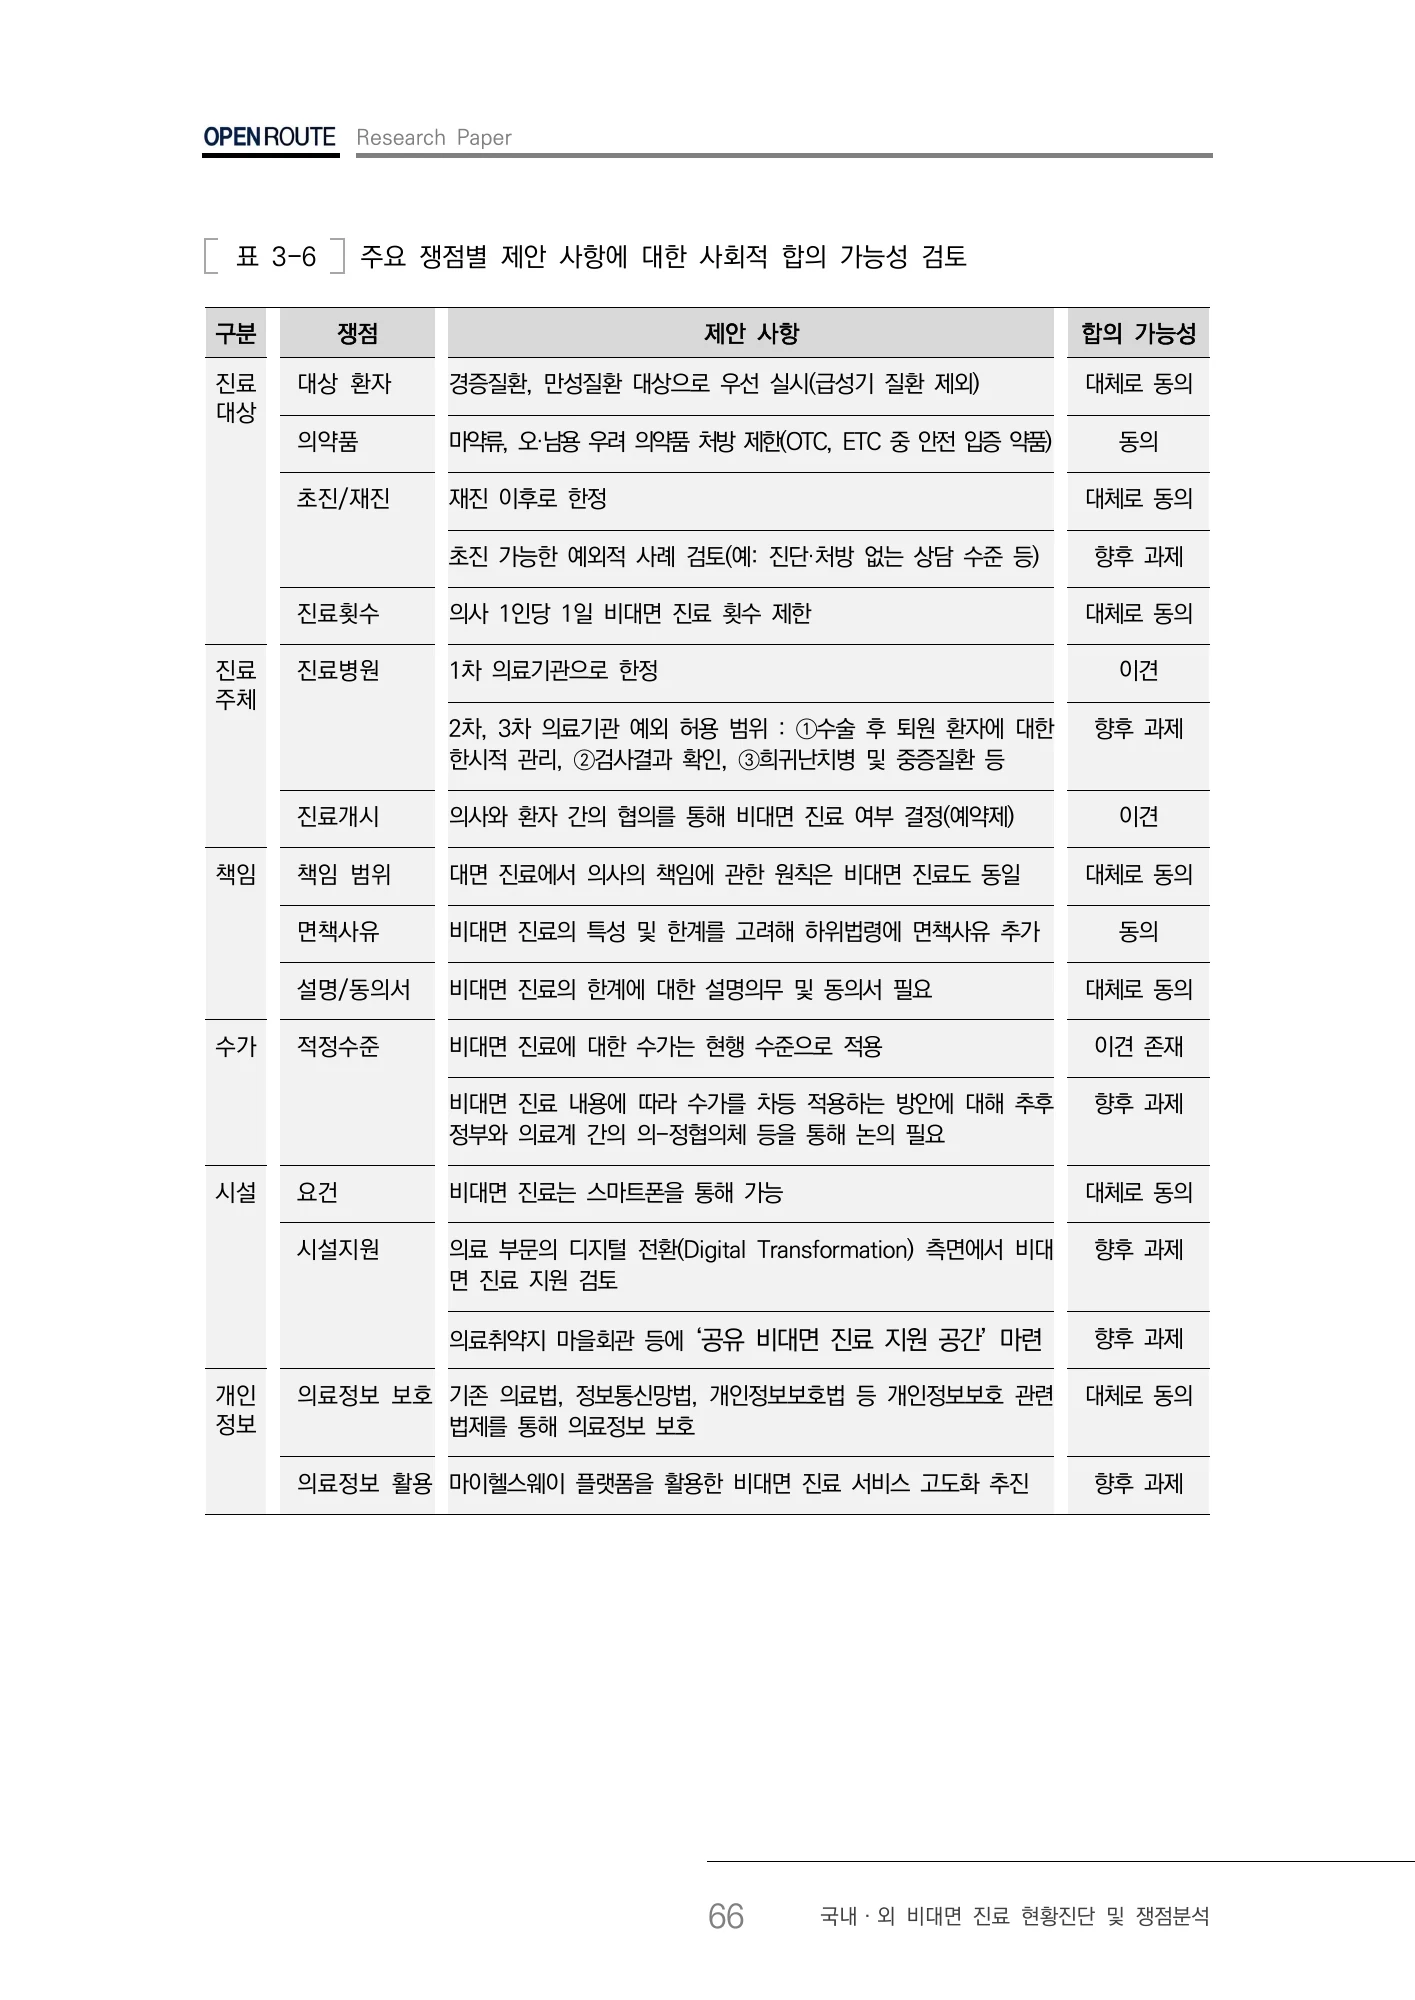
표3-6은 경증·만성질환과 재진을 중심으로 우선 검토하는 방안, 오남용 우려 의약품 제한, 설명의무·동의서, 기존 개인정보보호 체계 활용 등에서 대체로 동의 가능한 부분을 정리한다. 반면1차 의료기관으로 한정할지, 진료 개시를 누가 어떻게 결정할지, 수가를 어느 수준으로 할지에는 이견이 남는다. 초진의 예외,2·3차 기관의 허용 범위와 인프라 지원은 후속 과제다. 여기서 합의 가능은 연구진의 자문결과 해석이며 실제 입법 합의나 임상적 안전성 인증을 획득했다는 결과가 아니다.
Table 3-6 identifies potential agreement on a limited initial scope, medication restrictions, explanation and consent, and using existing privacy frameworks. Disagreement remains over limiting provision to primary-care institutions, initiation and payment levels. Initial consultations, exceptions for larger hospitals and infrastructure support remain future work. Potential agreement is the researchers’ reading of consultation evidence, not completed legislation, a binding stakeholder settlement or certification of clinical safety.
PDF 파일 59, 65, 67, 69쪽PDF pages 59, 65, 67, 69
제도화 방향으로 제안한 묶음Proposed institutional package
연구진의 제안은 최소 기준부터 도입하고 경험과 사회적 논의를 통해 확대 여부를 검토하는 묶음이다. 의사·환자 본인확인, 비대면 방식의 한계 설명, 적절하지 않을 때 대면으로 전환할 장치, 진료기록 관리 등을 함께 고려한다. 수가는 당시 수준을 기초로 진료 시간과 난이도에 따른 차등 방안을 추가 논의하고, 플랫폼의 역할과 정보 활용 범위도 별도 과제로 구분한다. 이 내용은 보고서의 정책 대안이며 현행 진료지침·법률 자문이나 개인 환자가 따라야 할 처방으로 제시하는 것이 아니다.
The proposed package starts with minimum conditions and leaves expansion to experience and deliberation. It connects identity verification, explanation of limitations, transition to in-person care when appropriate and records management. Payment differentiation, platform roles and information use are separated as further questions. These are the report’s institutional options, not current clinical instructions, legal advice or a treatment recommendation for an individual patient.
PDF 파일 66, 67, 68쪽PDF pages 66, 67, 68
실행과 추가 검토의 순서Implementation and further work
실행 논의는 진료 대상과 책임의 최소 조건을 정하는 일, 정보보호·기기 관리를 준비하는 일, 접근성이 낮은 사람의 이용을 지원하는 일을 구분한다. 의료취약지 공유 지원 공간과 필요한 장비 지원, 환자 선택권과 상급병원 접근성은 향후 검토 대상으로 남긴다. 해설상으로는 제도화가 단순한 허용·금지 선택이 아니라 주체별 업무와 근거 수집을 동반하는 과제라는 점이 중요하다. 원문은 이 지원 공간이 이미 구축돼 효과를 달성했다거나 제안의 비용·효과가 검증됐다고 보고하지 않는다.
Implementation separates minimum eligibility and responsibility rules from privacy/equipment preparation and support for people with poor access. Shared support spaces, equipment funding and access to larger hospitals are future considerations. An interpretive point is that institutionalisation involves assigned responsibilities and evidence gathering, not just permission or prohibition. The report does not establish that these proposed spaces were built, achieved outcomes or passed a cost-effectiveness evaluation.
PDF 파일 68, 69, 70쪽PDF pages 68, 69, 70
이용량과 진료 효과는 다른 증거다Utilization and treatment effects are different evidence
표 2-11은 2020년 2월 24일부터 2022년 1월 5일까지 13,252개 기관, 3,523,451건과 진찰료 43,763,444천원을 제시한다. 진료건수·의료기관 수·청구액은 각각 다른 단위다. 재진 86.6%라는 본문 값도 진찰료 금액의 비중이므로 이를 재진 환자나 전체 진료건수 비중으로 바꾸어 인용하지 않는 것이 중요하다.
Table 2-11 covers 13,252 institutions, 3,523,451 visits and KRW43,763,444 thousand in fees between February 24, 2020 and January 5, 2022. These are different units. The quoted 86.6% follow-up figure concerns fee amounts, not unique patients or necessarily the visit share.
한시 허용은 감염병 상황의 안전·편의를 위한 예외였고 일부 시범사업은 접근이 어려운 대상에게 한정됐다. 서로 다른 제도에서 축적한 관측자료를 합쳐 전국 상시 제도의 효과로 단정하기 어렵다. 원문이 인용한 플랫폼의 전달체계 평가와 고령층 앱 접근 문제 역시 각각의 출처·관점으로 구분해야 한다.
Temporary pandemic permission and targeted pilots operate under different conditions. Their observations cannot simply be combined into the effect of a permanent nationwide system. Platform assessments and older users’ access difficulties also retain distinct sources and perspectives.
PDF 파일 37, 38, 39, 40, 43쪽PDF pages 37, 38, 39, 40, 43
누가 결정하고 책임지는지에서 이견이 갈린다Disagreement concerns decision rights and responsibility
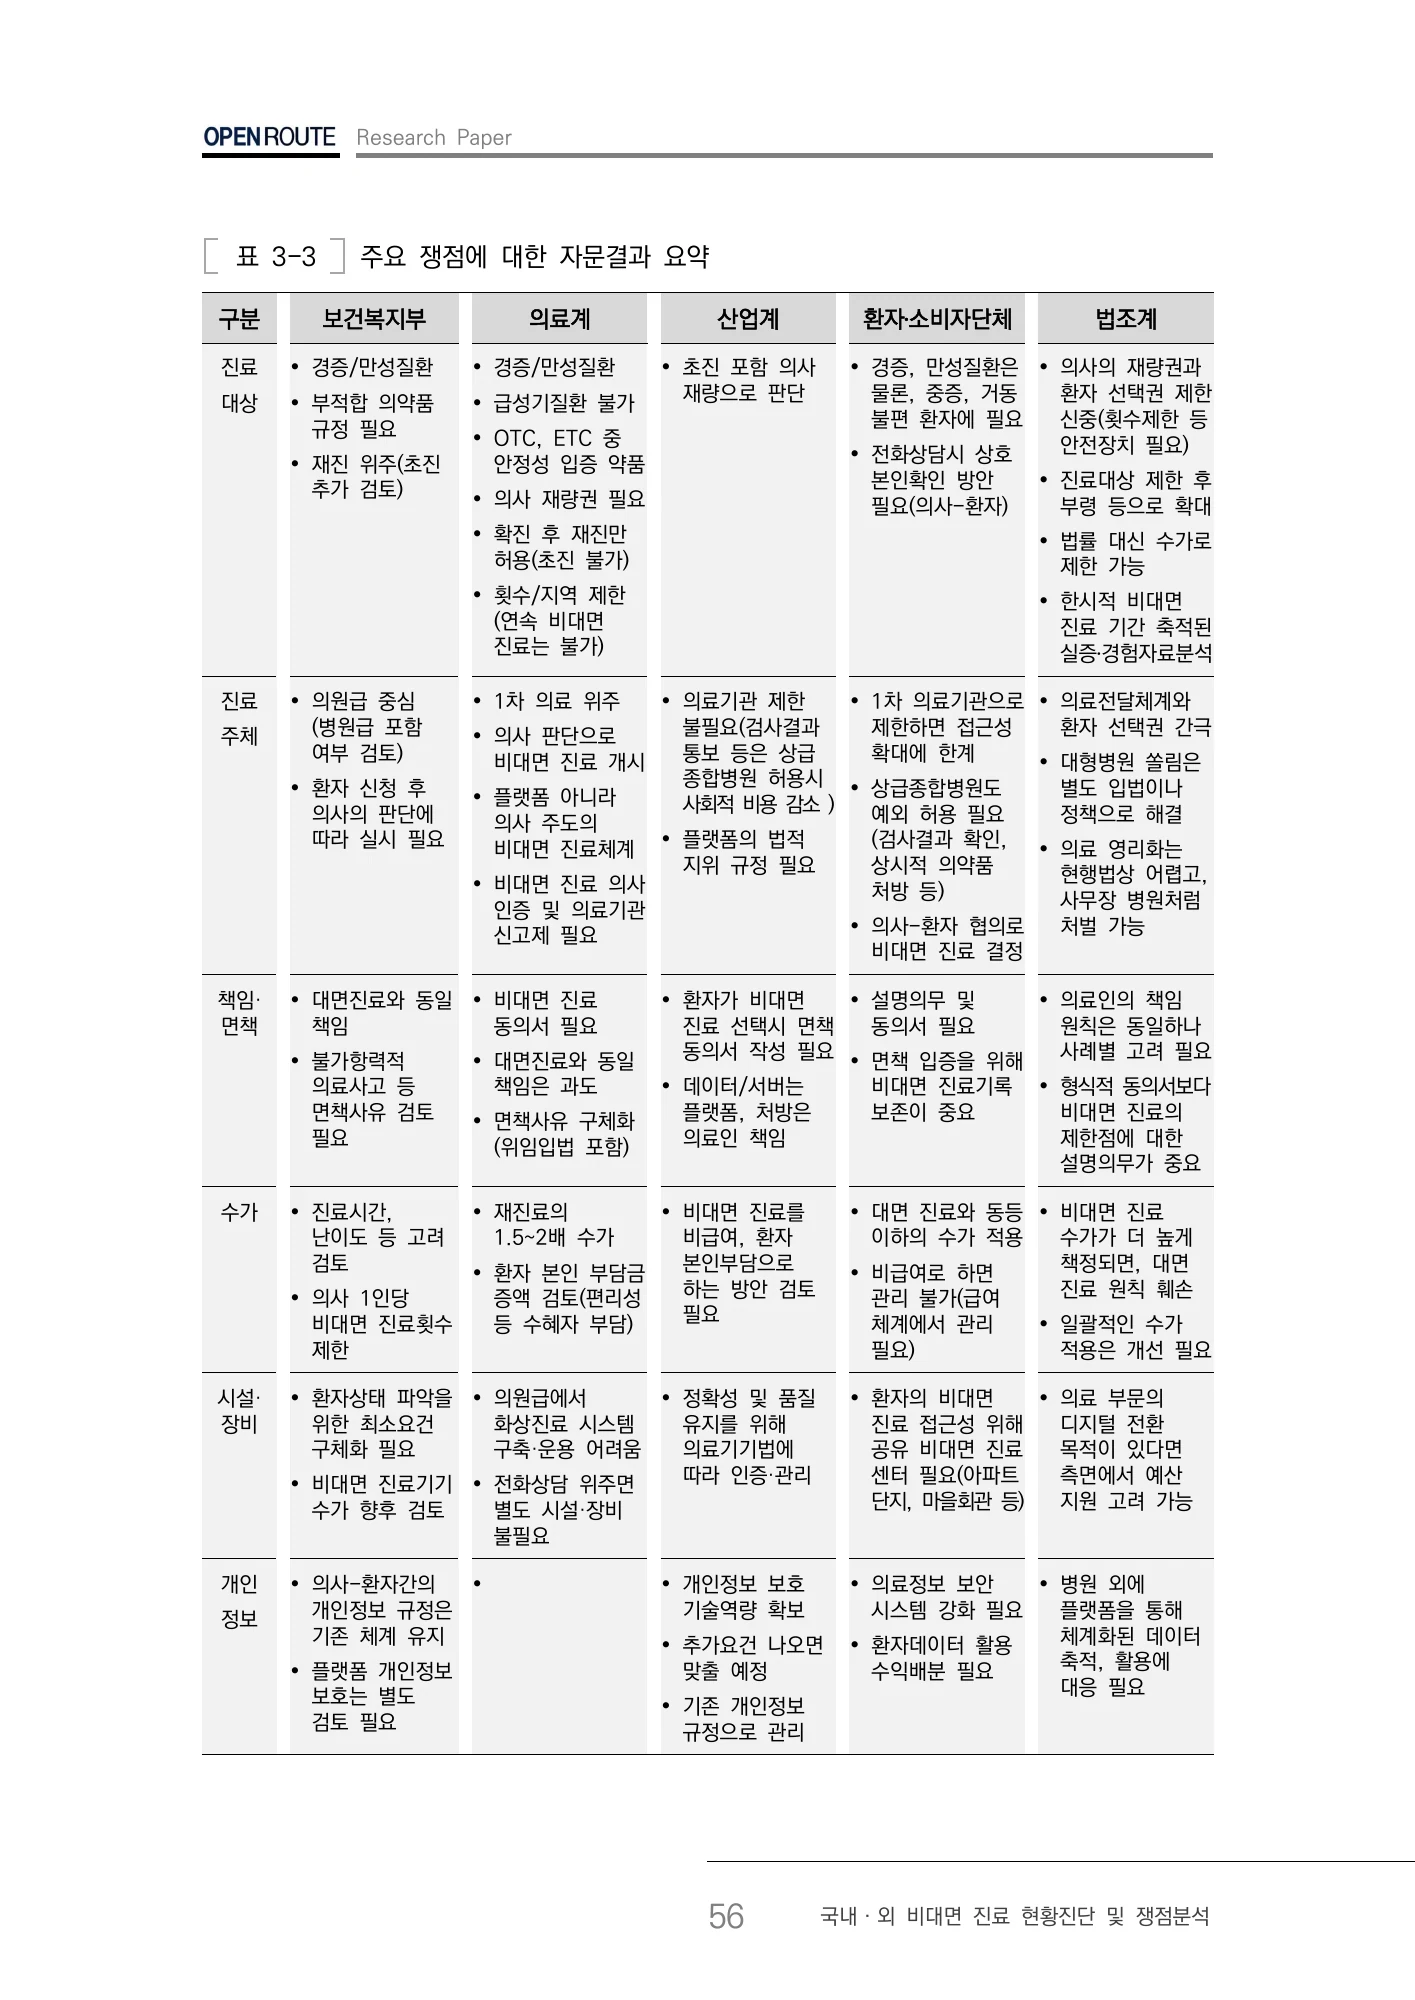
의료계는 재진·1차기관 중심과 책임 완화를, 산업계는 의사 재량의 초진과 기관 제한 완화를, 환자·소비자 쪽은 필요한 상급병원 접근과 낮은 수가를 강조한다. 같은 접근성이라는 말 아래 이용자의 선택, 진료 안전과 의료전달체계에 두는 우선순위가 다르다. 자문 비교는 집단 전체의 통계적 선호가 아니라 참여 단체·전문가의 입장을 정리한 자료다.
Medical participants emphasize follow-up/primary care and liability relief; industry emphasizes discretion and fewer provider restrictions; patient/consumer participants emphasize needed access and lower fees. These are consulted positions with different priorities, not representative population estimates for each sector.
책임 논의는 형식적 동의서만 받으면 면책된다는 구조가 아니다. 원문은 비대면 한계와 계획을 설명하고 기록을 보존하며 적합하지 않을 때 대면으로 전환하는 판단을 강조한다. 동시에 기기·플랫폼 장애와 의사의 진단·처방 책임을 나누어 검토한다. 시설 지원·공유 공간과 수가의 구체화는 향후 논의로 남겨 실행 성과로 서술하지 않는다.
Responsibility is not reduced to obtaining a form. The report emphasizes explanation, records and switching to in-person care when appropriate, while separating device/platform issues from diagnostic responsibility. Infrastructure support, shared spaces and detailed payment design remain future work, not achieved results.
PDF 파일 62, 63, 64, 65, 67, 68, 70쪽PDF pages 62, 63, 64, 65, 67, 68, 70
핵심 결과를 표로 읽기Read the key results in tables
| 쟁점Issue | 보고서 제안Report proposal | 원문 평가Source assessment |
|---|---|---|
| 진료 범위Initial scope | 경증·만성, 재진 중심Mild/chronic conditions; follow-up focus | 대체로 동의Broad potential agreement |
| 기관 범위Institution scope | 1차 의료기관 한정Primary-care limitation | 이견Disagreement |
| 초진 예외Initial-visit exceptions | 추가 사례 검토Further case review | 향후 과제Future work |
| 수가Payment | 당시 수준에서 구체화Refine from the historical level | 이견·추가 논의Disagreement; further discussion |
| 개인정보Privacy | 기존 법제 활용Use existing frameworks | 대체로 동의Broad potential agreement |
원문 표3-6을 선별했다. 합의 가능성을 평가한 제안이며 시행 완료나 임상 성과가 아니다.Selected from Table 3-6: consultation-based assessments, not implemented rules or clinical outcomes.
이 표를 읽는 방법How to read this table
대체로 동의·이견·향후 과제는 표결로 산출한 찬성률이 아니라 자문 결과에 대한 연구진의 종합 평가다. 특히 경증·만성·재진의 최소 범위에 관한 동의가 모든 초진·중증·기관 확대에 관한 동의를 뜻하지 않는다.Broad agreement/disagreement/future work are the researchers’ synthesis of consultation, not voted approval percentages. Agreement on minimum mild/chronic follow-up scope does not imply consensus on all first visits, severe conditions or provider expansion.
개인정보의 기존 법제 활용과 플랫폼 의료정보 활용은 원문에서도 별도 논점이다. 전자에 동의했다고 후자의 자유로운 이용까지 합의한 것은 아니다. 수가·장비·기관 범위의 이견을 지우지 않고 남기는 것이 후속 정책 선택에 필요한 정보다.Using existing privacy frameworks differs from permitting platform use of medical data. Agreement on one does not imply agreement on the other. Retaining disputes over fees, equipment and provider scope is part of the policy result.
PDF 파일 64, 65, 67, 68, 69쪽PDF pages 64, 65, 67, 68, 69
원문 해당 쪽의 내용을 선별·재구성한 해설 표Explanatory reconstruction of the cited source pages · PDF 파일 69쪽PDF page 69
| 기관 유형Provider type | 진료건수Visits | 진료건수 비중Share of visits | 진찰료: 천원Fees: KRW thousand |
|---|---|---|---|
| 의원급Clinics | 2,780,485 | 78.9% | 33,712,297 |
| 상급종합병원Tertiary hospitals | 247,074 | 7.0% | 3,792,016 |
| 종합병원General hospitals | 302,433 | 8.6% | 4,080,419 |
| 병원급 소계Other hospital subtotal | 193,459 | 5.5% | 2,178,714 |
표 2-11의 2020.2.24–2022.1.5 진료분이다. 총 3,523,451건이며 고유 환자 수가 아니다. 청구액 세부 합계와 총계에는 천원 단위 반올림 차이가 있다. 현재 이용량·안전성·치료 효과를 나타내지 않는다.From Table 2-11, February 24, 2020–January 5, 2022. Total visits are 3,523,451, not unique patients. Fee components differ slightly from the total through rounding. These are not current use or clinical safety/effectiveness estimates.
원문 표 2-11Original Table 2-11 · PDF 파일 38쪽PDF page 38
원문의 핵심 표·그래프Key tables & figures in the source
표·그림이 수록된 원문 페이지입니다. 이미지를 누르면 확대할 수 있습니다.Original pages containing the selected tables or figures. Select an image to enlarge it.
한시 허용의 기관·진료·청구액 구성Temporary-period institutions, visits and fees
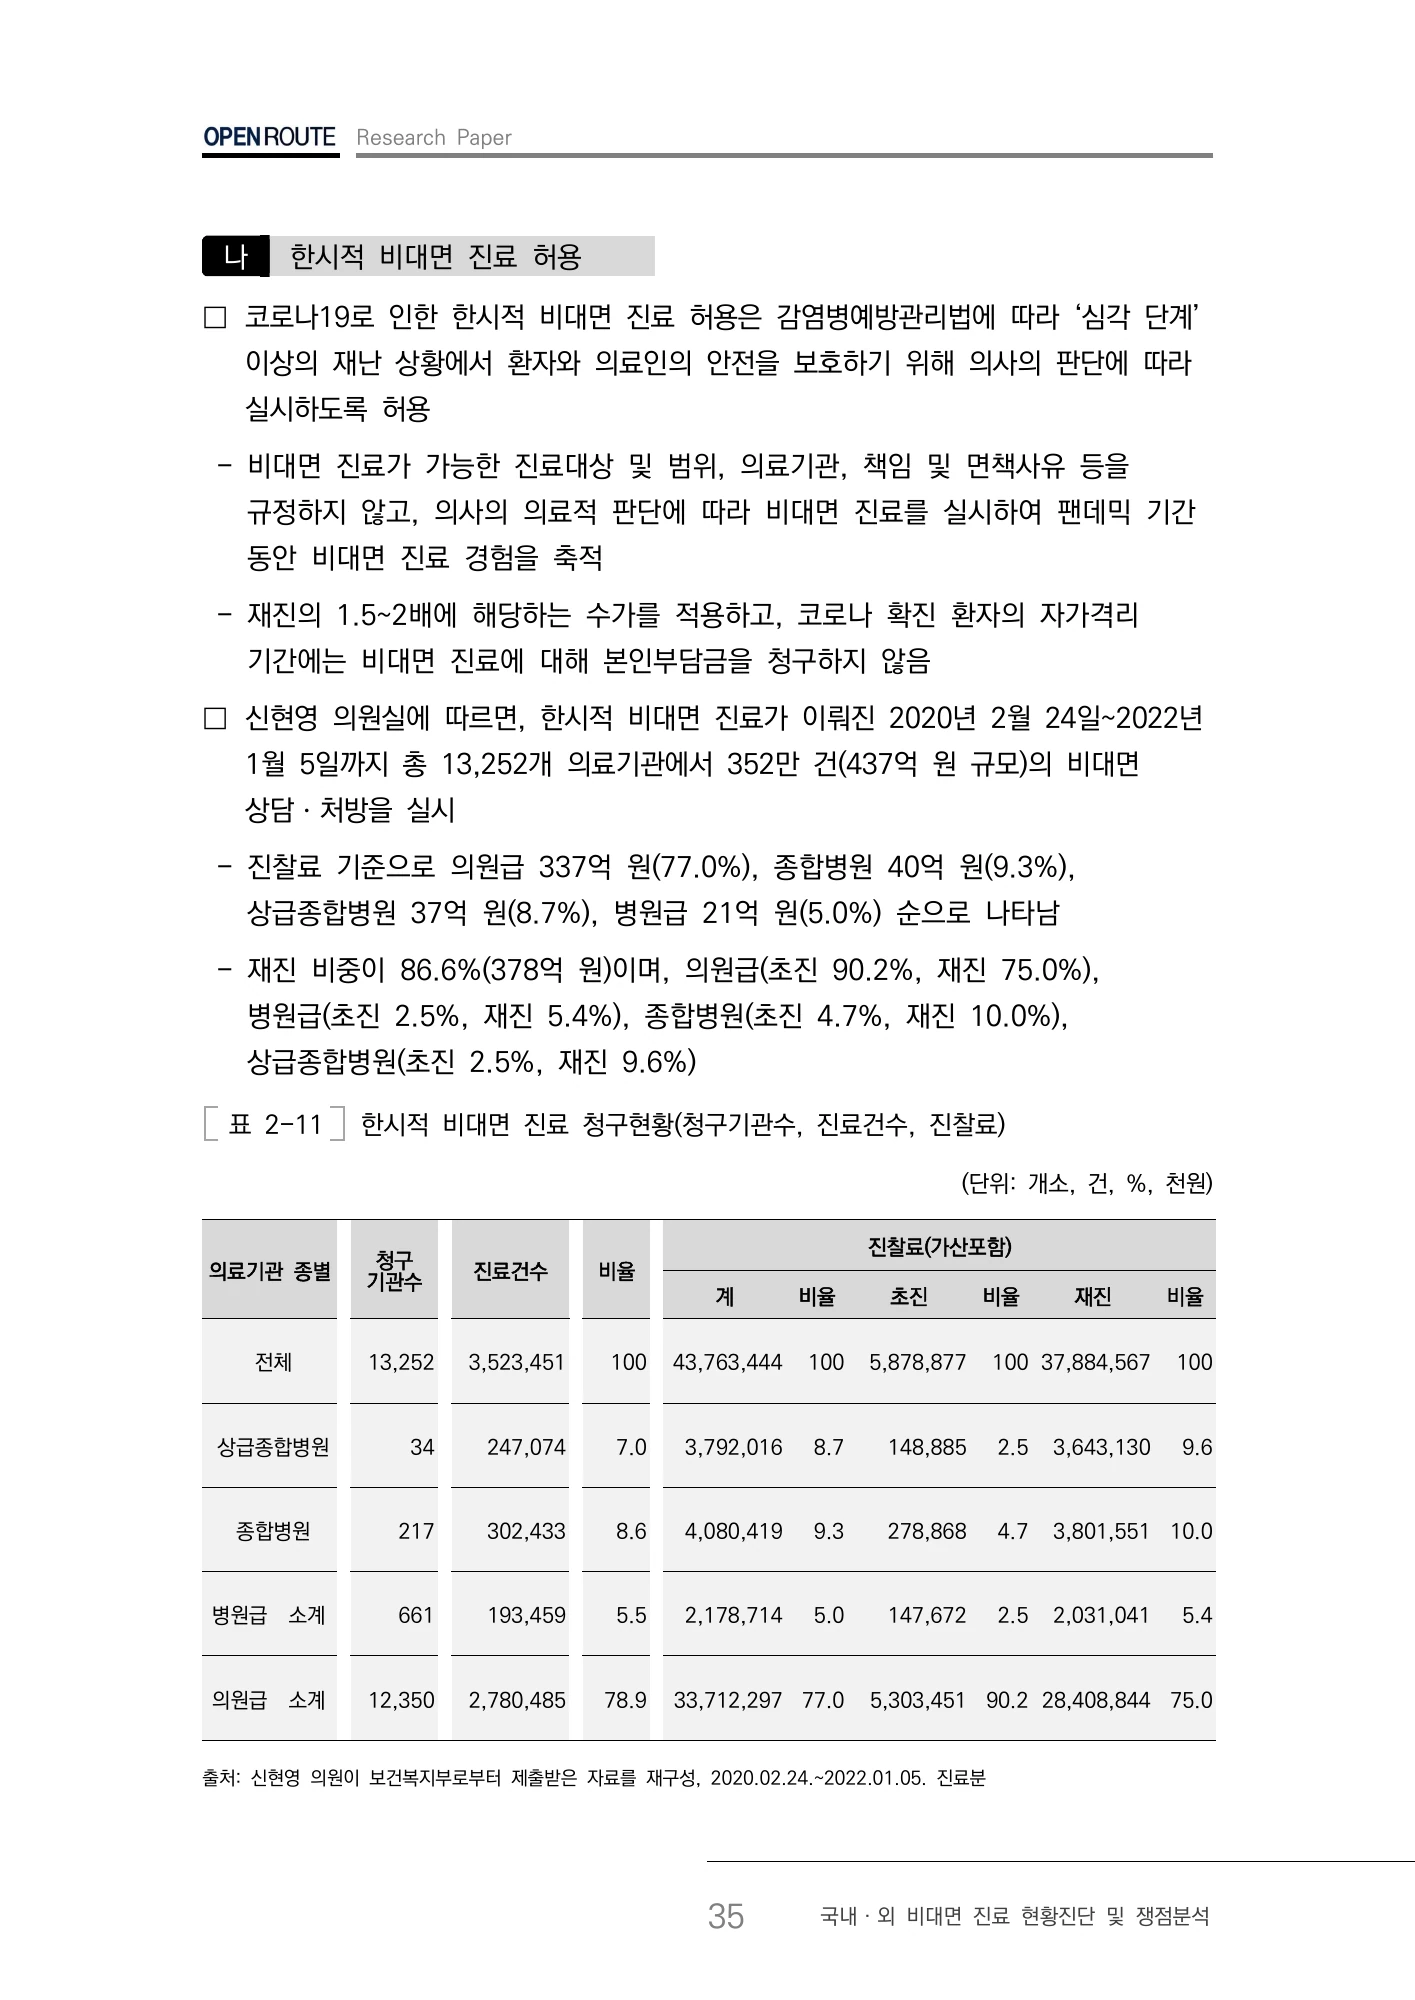
표3-3 이해관계자 자문 비교Table 3-3: stakeholder positions
이해관계자별 핵심 쟁점 비교Stakeholder comparison across key issues
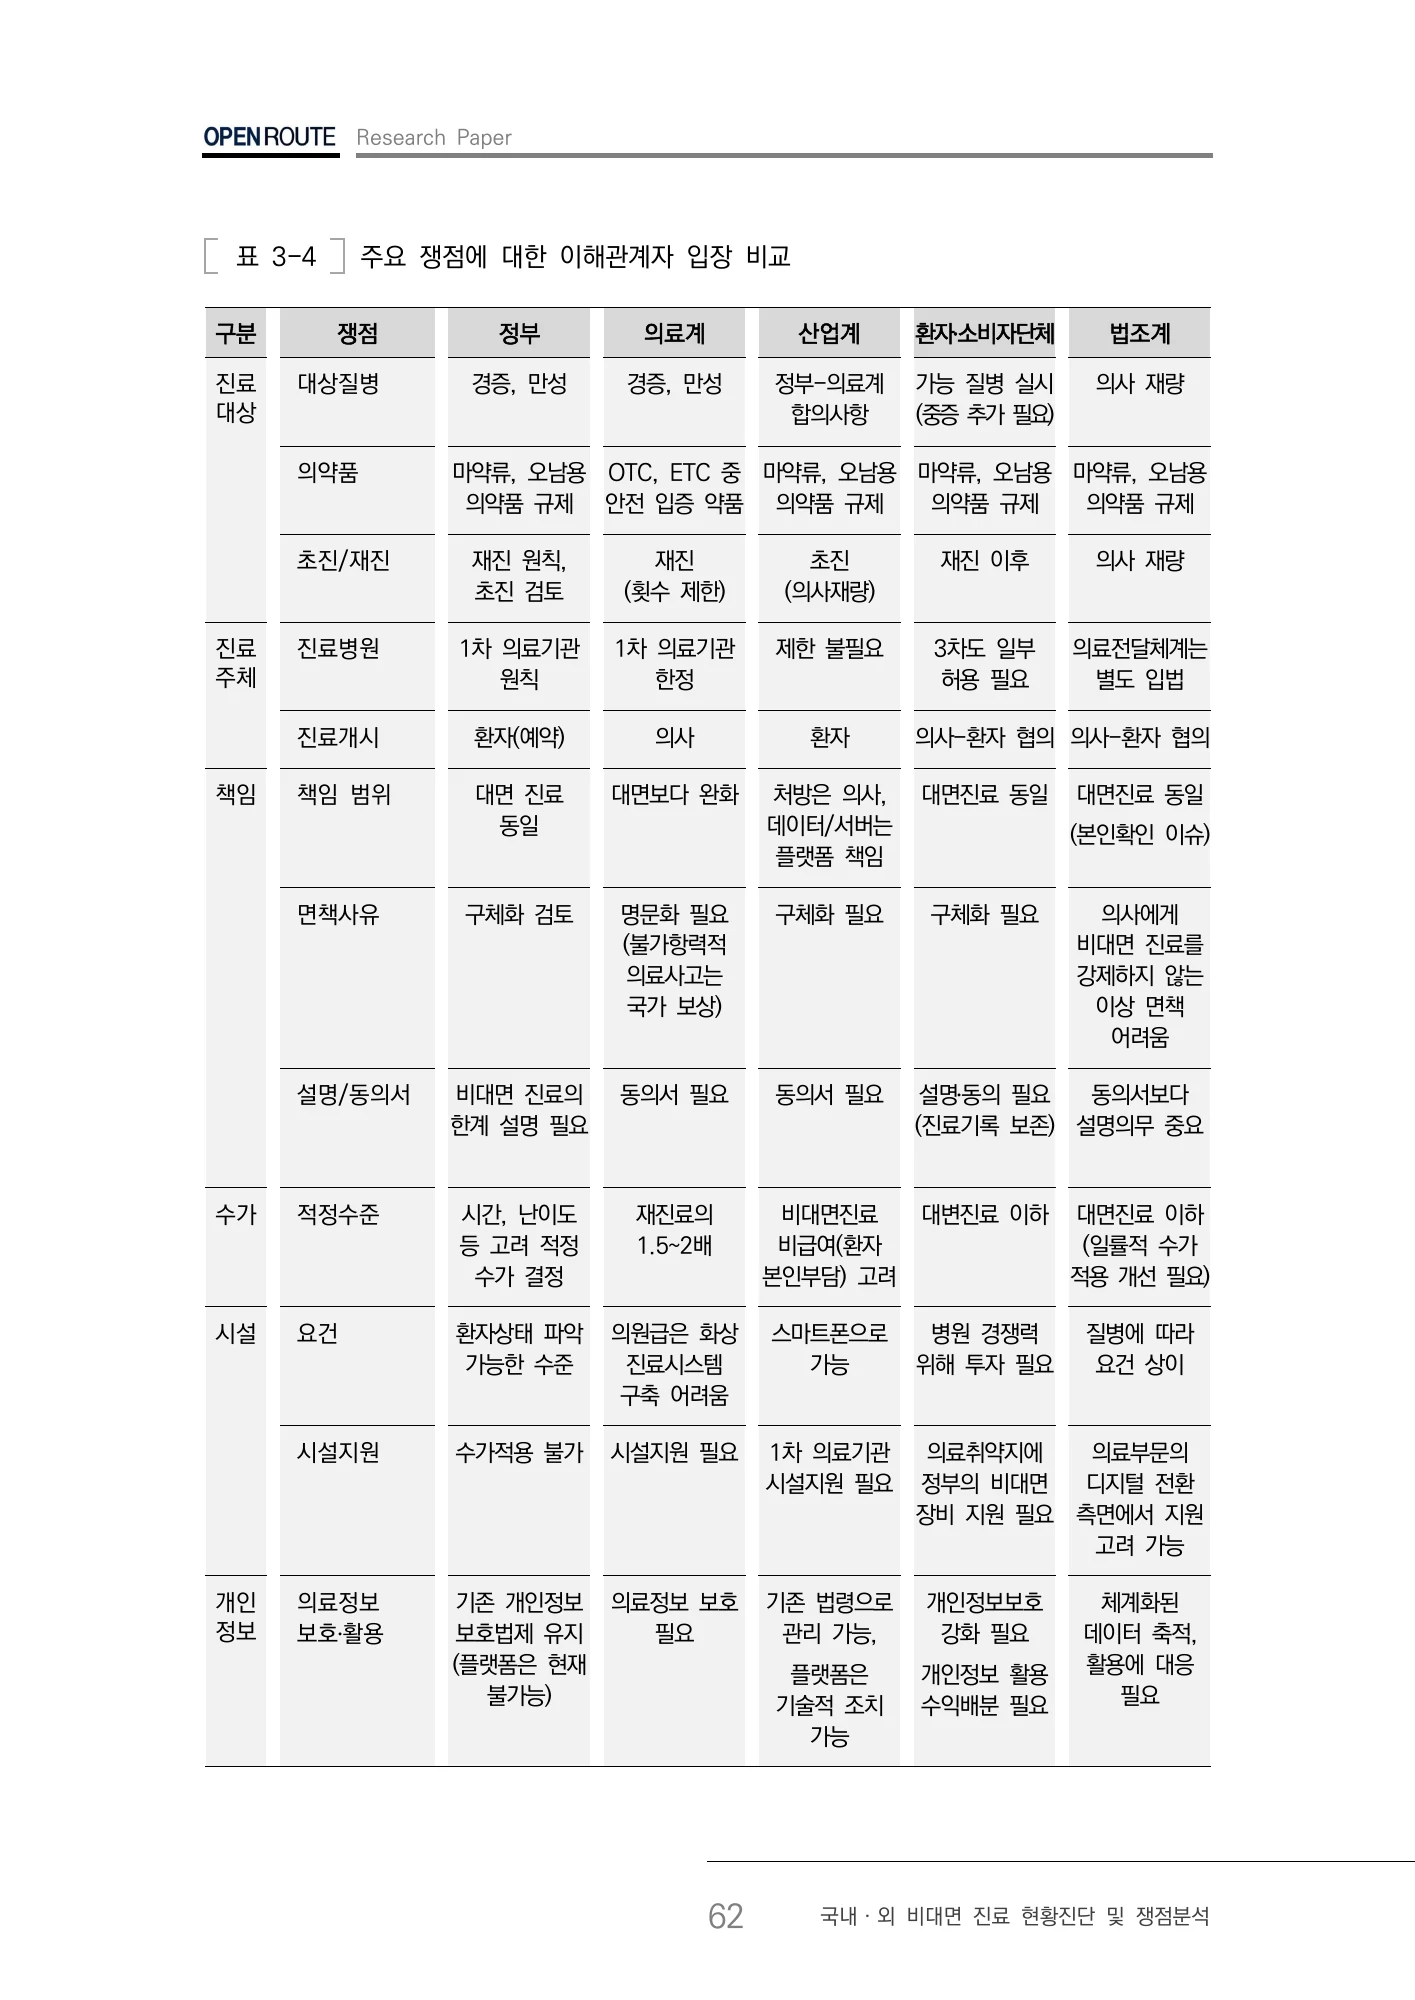
표3-5 제도화 방향 제안Table 3-5: proposed institutional direction
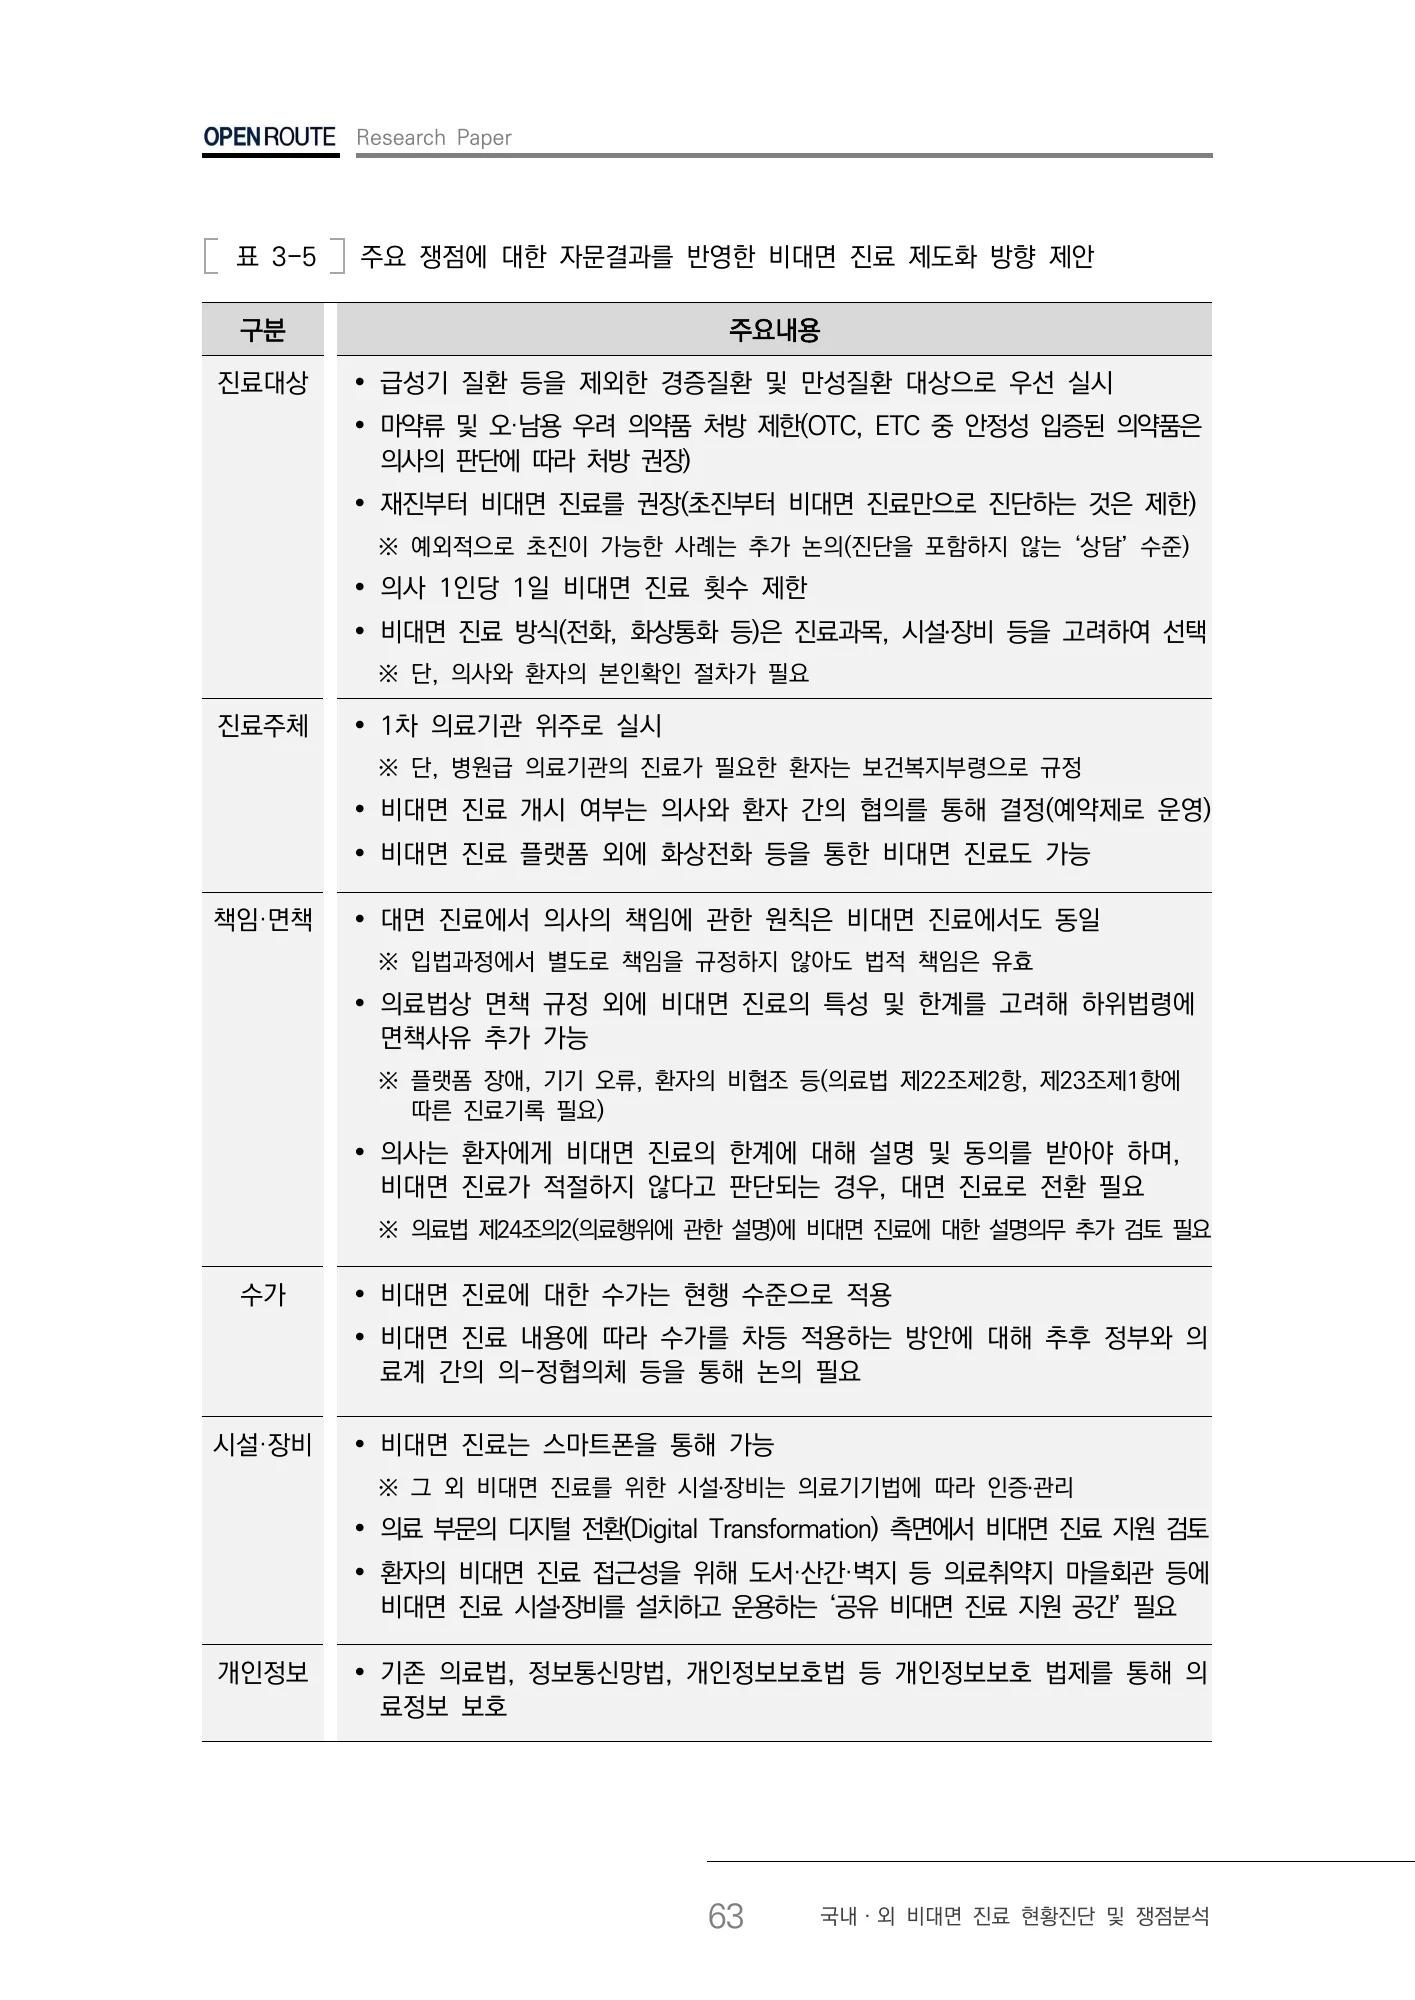
표3-6 합의 가능성Table 3-6: potential agreement
해석의 범위와 미확인 사항Limits and unresolved issues
이 보고서는2022년의 제도·사례와 자문을 정리한 연구로 현재 의료정책의 상태를 확정하는 자료가 아니다. 시범사업·해외 사례의 성과는 원자료를 재분석하지 않았고 FGI로 치료 효과의 크기나 위험을 계산하지 않았다. 자문 참여자와 질문 구성에 따른 한계도 고려해야 한다. 웹 해설에서는 이해관계자의 의견, 연구진의 제안, 외부 관측자료를 구분해 적었으며 모든 쪽의 사실·법령이 현재도 유효하다는 의미로 제시하지 않는다. 개인 참여는 확인됐지만 원문 전체를 단독 연구실적으로 바꾸어 설명하지 않는다.
This is a historical 2022 policy and consultation study, not confirmation of current medical policy. It does not reanalyse pilot or foreign clinical data or estimate treatment effects through interviews. Participant selection and question framing also matter. This explanation separates stakeholder views, proposals and external observations; it does not certify every historical legal or factual statement as current. Documented participation is preserved without converting a collaborative report into sole authorship.
PDF 파일 2, 37, 50, 68, 70쪽PDF pages 2, 37, 50, 68, 70
근거 쪽: Evidence pages: 2, 3, 5, 6, 16, 28, 37, 38, 39, 40, 43, 45, 50, 59, 62, 63, 64, 65, 66, 67, 68, 69, 70 · PDF 파일 기준, 인쇄 쪽수와 다를 수 있습니다. · PDF file pagination may differ from printed page numbers.
근거와 검토 범위Source and review scope
73쪽의 제공된 원문 자료를 기준으로 본문·표·선정 이미지를 확인했습니다. 해설은 연구 내용을 새 문장으로 정리했으며, 실제 원문 페이지를 함께 실었습니다. 분석 결과의 독립 재현이나 기관의 공식 입장 확인을 뜻하지 않습니다.
The text, tables and selected images were checked against the 73-page source document supplied for this site. This guide is an editorial summary accompanied by original source pages. This does not imply independent replication or institutional endorsement.
확인한 PDF 쪽: Source PDF pages: 1, 2, 3, 5, 6, 16, 28, 37, 38, 39, 40, 43, 45, 50, 59, 61, 62, 63, 64, 65, 66, 67, 68, 69, 70